Movement & Strength
Muscle Mass and Longevity:
Why Sarcopenia Is an Aging Problem, Not Just a Bodybuilding One
Muscle tends to be thought of as either a vanity concern or an athletic one — something for gym-goers, not a genuine medical priority. This article, the anchor piece for our Movement & Strength series, makes the case that this framing is genuinely outdated. Skeletal muscle is now understood to function as an active hormone-producing organ, sarcopenia has a formal clinical definition with real diagnostic criteria, and the rate of muscle loss with age is precisely quantified — making this one of the more measurable, modifiable levers in longevity medicine, not a cosmetic afterthought.
Quick Summary
- Sarcopenia has a formal, three-tier clinical definition — the 2019 European consensus (EWGSOP2) identifies low muscle strength as the primary indicator, confirms diagnosis via low muscle quantity or quality, and uses poor physical performance to classify severity, not muscle appearance alone
- Muscle loss follows a well-quantified, accelerating timeline — roughly 8% per decade from early adulthood until age 70, then accelerating to 13-24% per decade afterward
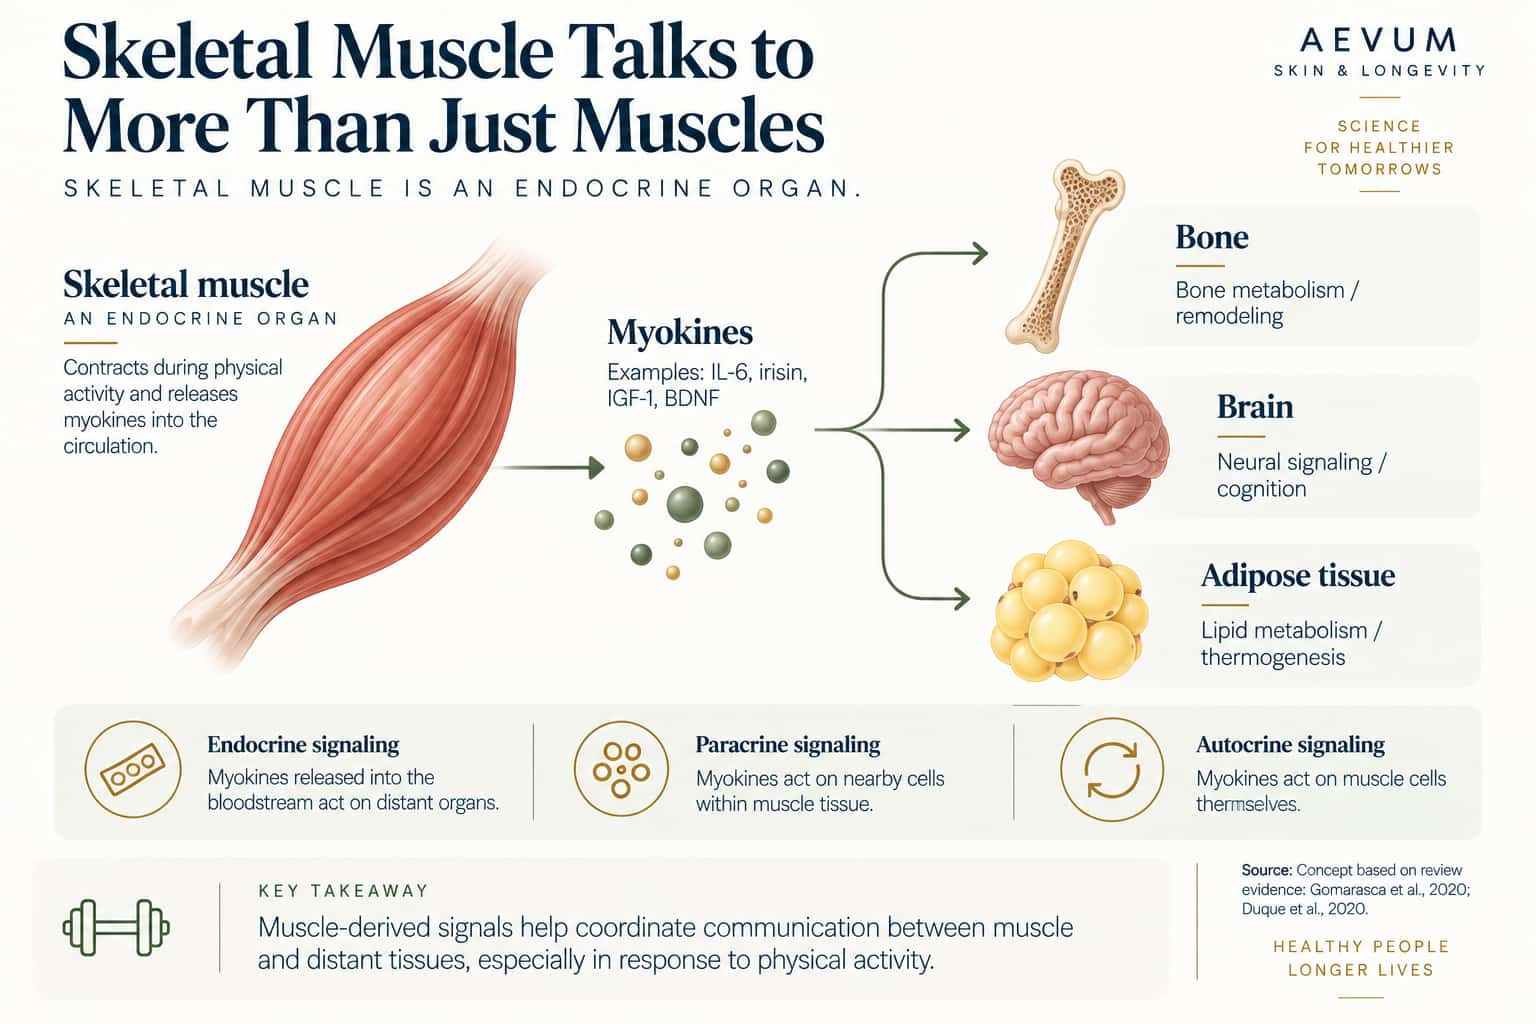
- Skeletal muscle is now recognised as a genuine endocrine organ, secreting over 600 identified signalling peptides called myokines that communicate directly with bone, brain, and fat tissue — a role entirely separate from movement itself
- Muscle is the body's primary site for clearing glucose from the bloodstream — responsible for roughly 75-80% of insulin-mediated glucose disposal after a meal, directly linking muscle mass to metabolic and diabetes risk
- Low muscle mass and strength are independently associated with increased mortality risk across multiple studies, not just reduced quality of life or mobility
Key numbers at a glance
| Measure | Figure |
|---|---|
| Muscle mass decline, per decade, up to age 70 | ~8% |
| Muscle mass decline, per decade, after age 70 | ~13-24% |
| Myokine peptides identified to date | 600+ |
| Share of insulin-mediated glucose disposal handled by muscle | ~75-80% |
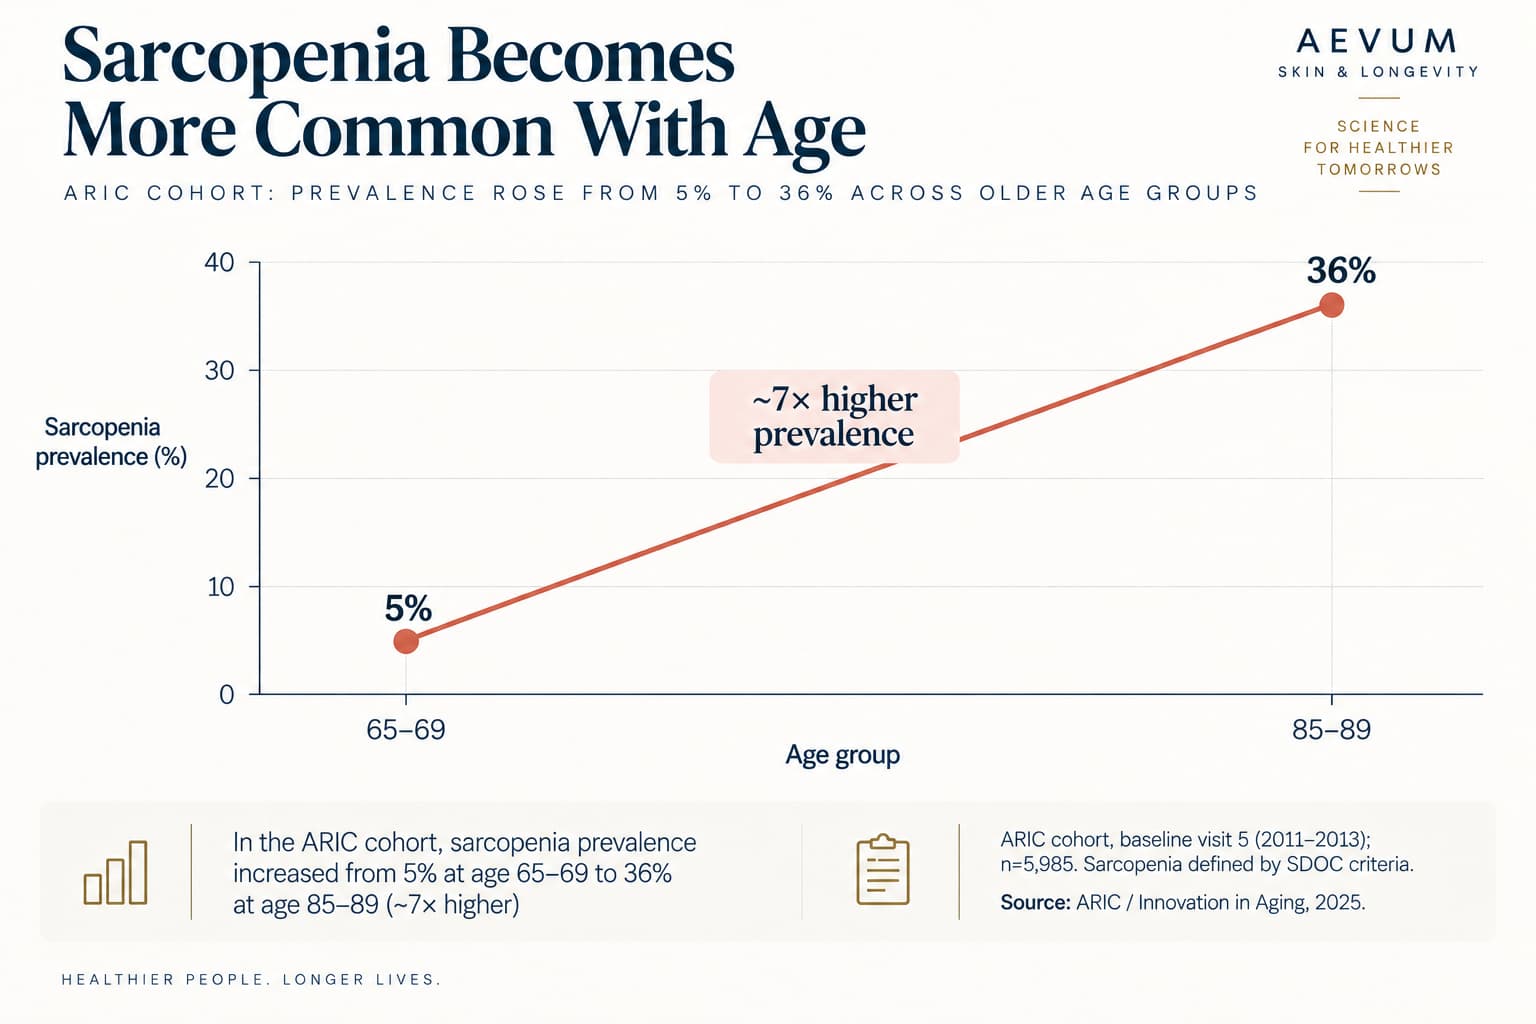
| Sarcopenia prevalence, ages 65-69 vs. 85-89 (large US cohort) | 5.0% vs. 36.0% |
How it works: what sarcopenia actually is, and why muscle matters beyond movement
Sarcopenia is a formally defined clinical condition, not an informal description of "getting weaker with age." The 2019 revised European consensus definition (EWGSOP2) reframed sarcopenia around three distinct components: low muscle strength as the primary, most clinically relevant indicator; low muscle quantity or quality used to confirm the diagnosis; and poor physical performance (such as slow gait speed) used to classify severity once sarcopenia is confirmed. This shift — prioritising strength and function over raw muscle size alone — reflects a genuine evolution in understanding: how much force muscle can actually produce predicts outcomes better than how much muscle tissue is simply present.
The rate of decline is genuinely well-quantified, and it isn't linear. Muscle mass loss begins in early-to-mid adulthood and proceeds at roughly 8% per decade until around age 70, at which point the rate of loss accelerates substantially, to somewhere between 13% and 24% per decade. This acceleration point matters practically — it means the muscle lost in a single decade after 70 can exceed what was lost across two or three earlier decades combined, making the years leading up to this inflection point a genuinely higher-leverage window for prevention than most people assume.
Muscle functions as a genuine endocrine organ, not just contractile tissue. Over the past two decades, research has established that skeletal muscle — the largest organ in the body by mass — secretes signalling molecules called myokines, with more than 600 distinct peptides identified so far. These myokines carry out autocrine, paracrine, and endocrine functions, meaning they act locally within the muscle itself and also travel through the bloodstream to communicate with bone, brain, and adipose tissue. Interleukin-6 (IL-6) is a particularly instructive example of this system's complexity: chronically elevated IL-6 from obesity-related inflammation is genuinely harmful, but the IL-6 released acutely by contracting muscle during exercise has a different, beneficial signalling role — increasing insulin-stimulated glucose disposal and stimulating fat oxidation. The same molecule, produced by different tissue under different conditions, plays essentially opposite roles — a genuinely important nuance for understanding why muscle contraction itself, not just muscle mass at rest, carries real physiological weight.
Muscle is central to metabolic health specifically. Skeletal muscle is responsible for roughly 75-80% of the body's insulin-mediated glucose disposal following a meal — making it, by a wide margin, the body's primary tissue for clearing blood sugar. This creates a direct, mechanistic link between muscle mass and diabetes risk: less muscle tissue means less capacity to clear glucose from the bloodstream, independent of diet.
What the research shows
Sarcopenia prevalence rises sharply with age, and precisely how much depends heavily on which definition is used. A large, recent US cohort (the ARIC study) tracking adults from age 65 into their 90s found sarcopenia prevalence rising from 5.0% at ages 65-69 to 36.0% at ages 85-89 — a clear, substantial age gradient using modern diagnostic criteria. It's worth knowing that prevalence estimates vary considerably depending on which definition and cutoff values are applied: a direct comparison study found male sarcopenia prevalence of 31.9% using the original 2010 criteria versus just 12.0% using the revised 2019 EWGSOP2 criteria in the same population — a genuinely large difference driven by updated handgrip strength thresholds, illustrating that diagnostic criteria in this field are still actively being refined, not a settled, unchanging standard.
Sarcopenia is independently associated with increased mortality risk. Across the sarcopenia literature generally, low muscle mass and low muscle strength are consistently associated with increased falls, fractures, physical disability, and mortality. One prospective study of elderly patients found sarcopenia, diagnosed via EWGSOP2 criteria, associated with roughly three times higher all-cause mortality risk over a 24-month follow-up — worth noting this specific figure comes from a higher-risk hemodialysis population rather than the general public, but the broader directional finding (sarcopenia predicting mortality) is consistently replicated across many studies in less severely ill populations too.
Recommendations by life stage
- 1Adults in their 20s and 30s
Given that muscle mass is likely near its lifetime peak during this window, and that the roughly 8%-per-decade decline begins from here rather than starting later, this is the highest-leverage period for building a genuine muscular reserve — resistance training habits established now pay dividends well beyond this decade.
- 2Adults in their 40s to 60s
This window sits before the sharp post-70 acceleration in muscle loss — a genuinely important period to establish or maintain consistent resistance training, given how much steeper the decline becomes afterward.
- 3Adults over 70
Given the substantially higher rate of loss and sarcopenia prevalence in this group, this is the population where the mortality and disability stakes are most immediate — muscle-focused intervention remains genuinely valuable even later in life, not merely preventive at this stage.
- 4Anyone with metabolic health concerns, prediabetes, or type 2 diabetes
Given muscle's role in the large majority of the body's glucose disposal, maintaining or building muscle mass is a direct, mechanistic lever relevant to blood sugar management.
Practical notes
- Sarcopenia is a real, formally diagnosed clinical condition with specific strength, quantity, and performance criteria — not an informal description of ageing
- Muscle loss accelerates sharply after age 70 — the years before this inflection point are a genuinely higher-leverage window for building reserve than commonly assumed
- Muscle functions as a hormone-producing organ, not just tissue for movement — the same signalling molecule (IL-6) can be harmful or beneficial depending on whether it's chronically elevated or acutely released through exercise
- Muscle handles the large majority of the body's blood sugar clearance — a direct, often underappreciated connection between muscle mass and metabolic health
- Diagnostic criteria for sarcopenia are still evolving — don't be surprised if prevalence figures vary considerably between studies using different definitions
Muscle mass is one of the more genuinely measurable, modifiable levers in longevity medicine — with a formal clinical definition, a precisely quantified decline rate, and a growing understanding of its role as an active signalling organ well beyond movement alone. For the single best test of muscle function specifically, see our Grip Strength article, and for how much training is actually needed to build and preserve muscle, see our Resistance Training content elsewhere in this series. If you'd like a clearer picture of your own muscle health as part of a broader longevity assessment, our Longevity Doctors offer a free consultation as a starting point.
- Cruz-Jentoft AJ, Bahat G, Bauer J, et al. Sarcopenia: revised European consensus on definition and diagnosis. Age and Ageing, 2019;48(1):16-31.
- Ali S, Garcia JM. Sarcopenia, cachexia and aging: diagnosis, mechanisms and therapeutic options — a mini-review. Gerontology, 2014.
- Sarcopenia Incidence From Age 65 to 90+ Years From 2011 to 2023 in the ARIC Cohort. Innovation in Aging, 2025.
- Impact of using the updated EWGSOP2 definition in diagnosing sarcopenia: A clinical perspective. 2020.
- Merz KE, Thurmond DC. Role of Skeletal Muscle in Insulin Resistance and Glucose Uptake. Comprehensive Physiology, 2020.
- Severinsen MCK, Pedersen BK. Muscle-Organ Crosstalk: The Emerging Roles of Myokines. Endocrine Reviews, 2020.
- Sarcopenia and Mortality in Older Hemodialysis Patients. 2022.
Free longevity assessment
How does your muscle health
score on your longevity assessment?
Take the free Aevum Protocol assessment to see how your movement & strength and 6 other longevity domains are performing — and get a personalised 90-day plan.
Take the free assessment